Contentsexpand_more
- Does a Toothache Go Away with Antibiotics?
- When Do Antibiotics Help Toothache?
- How Long Do Antibiotics Take to Work for Toothache?
- Antibiotics Not Working for Toothache: Primary Causes
- Wisdom Tooth Pain Antibiotics: Pericoronitis Management
- Common Types of Antibiotics for Tooth Infections
- The Hazards of Indiscriminate Antibiotic Use
- Factors Influencing Treatment Cost
- Antibiotics vs. NSAID Analgesics vs. Clinical Operative Care
- Frequently Asked Questions (FAQ)
- Can I buy antibiotics at a pharmacy to fix my toothache before seeing a dentist?
- Can a dentist extract a tooth or perform a root canal while it is actively abscessed?
- If my tooth pain stops after 3 days of antibiotics, can I stop taking the medication?
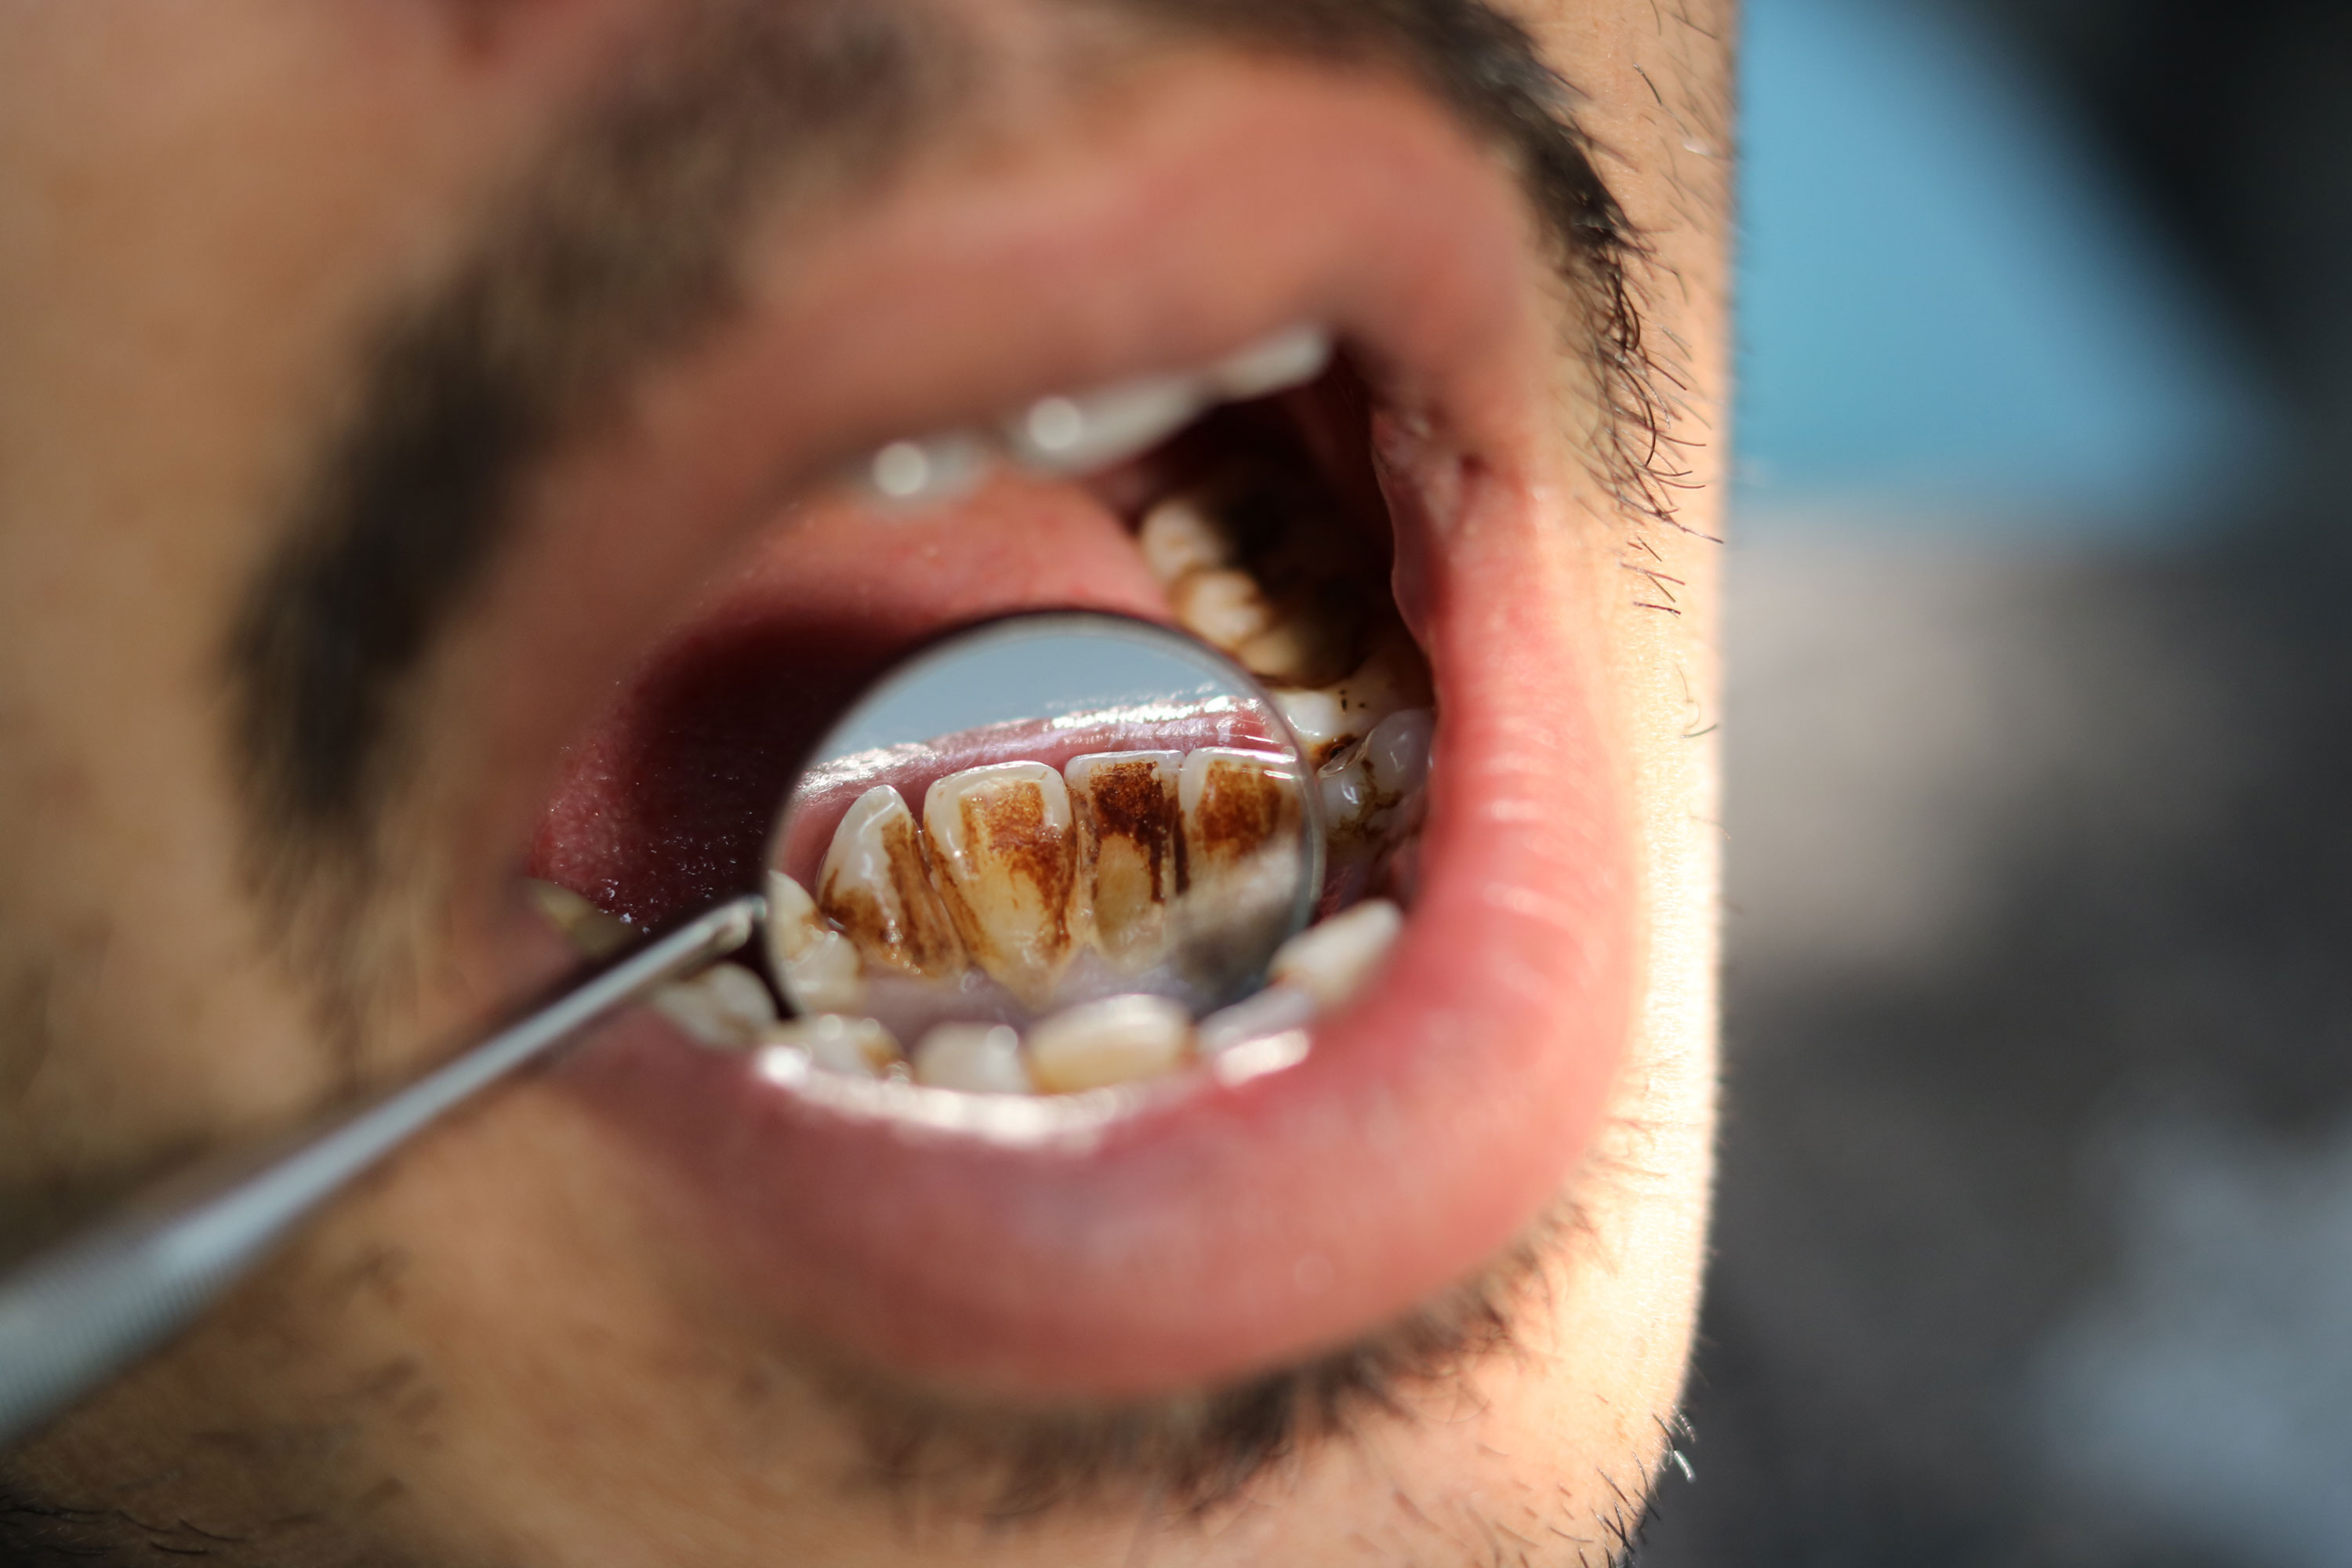
When severe, throbbing dental pain strikes unexpectedly, many individuals immediately search their medicine cabinets for leftover prescription pills, asking: "Do I have any spare antibiotics at home?" The widespread belief that taking a course of antibiotics will dissolve a tooth infection and cure a toothache permanently is one of the most common misconceptions in dentistry. Patients routinely discover that after ingesting several antibiotic tablets, the throbbing ache persists, prompting the concern: "Why are my antibiotics not working for a toothache?" In clinical pharmacology, the relationship between antibiotics for toothache is unambiguous: antibiotics are not analgesics; they do not block neural pain pathways and cannot eradicate mechanical bacterial decay inside a tooth.
The dental pulp resides within a rigid chamber encased by calcified dentin and enamel. When extensive caries breaches the pulp tissue, vascular thrombosis and tissue necrosis follow, terminating blood circulation inside the chamber. Because systemic antibiotics travel exclusively via blood vessels, an orally ingested antibiotic cannot enter a non-vital, necrotic pulp space. Consequently, even after days of medication, bacteria sequestered inside the root canal proliferate unchecked.
Does a Toothache Go Away with Antibiotics?
In clinical dentistry, the definitive answer to does toothache go away with antibiotics is: No, antibiotics do not directly relieve toothache pain.
The physiological factors underlying this include:
Antibiotics Lack Analgesic Mechanisms: Antibiotics are antimicrobial agents designed to inhibit bacterial cell wall synthesis or interrupt protein translation. They do not downregulate cyclooxygenase enzymes or block peripheral sensory pain impulses.
The Pulp Space Lacks Microvascular Perfusion: Once pulpal tissue dies, local microcirculation ceases. Orally administered antibiotics circulate through systemic vessels but cannot diffuse into the pulp chamber.
Mechanical Debridement is Essential: Unless an endodontist mechanically negotiates, shapes, and disinfects the contaminated canal spaces, or an oral surgeon extracts the tooth, the bacterial reservoir persists.
When Do Antibiotics Help Toothache?
Systemic antibiotics are never indicated for localized, uncomplicated pulpitis. Under American Dental Association (ADA) and FDI World Dental Federation guidelines, when do antibiotics help toothache is restricted to specific criteria:
Spreading Cellulitis and Extraoral Facial Swelling: The bacterial infection has penetrated the cortical bone plate, spreading into fascial spaces (producing visible swelling in the cheek, submandibular space, or orbit).
Systemic Manifestations of Infection: The localized dental issue is accompanied by fever (>38°C), malaise, lymphadenopathy, or systemic chills.
Trismus, Dysphagia, or Airway Compromise: Inability to open the jaw, difficulty swallowing, or respiratory compromise indicating impending fascial space infection (e.g., Ludwig's angina).
Immunocompromised Systemic Status: Patients with poorly managed diabetes, active chemotherapy, or immunosuppressive therapy where the risk of bacteremia demands prophylactic protection.
How Long Do Antibiotics Take to Work for Toothache?
Antibiotics require systemic absorption and distribution to achieve minimal inhibitory concentrations (MIC) in surrounding infected soft tissues. The clinical timeline for how long antibiotics take to work for toothache progresses as follows:
First 24 Hours: Serum levels rise and tissue saturation begins, but patients rarely experience symptomatic relief. Localized throbbing continues.
48 to 72 Hours (Days 2 to 3): Bacterial loads within external soft tissues decrease. If extraoral fascial swelling was present, tissue induration softens and tension-related pain subsides.
The Misconception of Total Resolution: Pain reduction at day 3 does not signify healing of the tooth. It merely indicates temporary suppression of extraradicular bacteria. Without mechanical root canal therapy, the infection will return aggressively once the antibiotic cycle ends.
Antibiotics Not Working for Toothache: Primary Causes
When patients report that antibiotics are not working for a toothache, diagnostic evaluation typically reveals one of the following factors:
Non-Bacterial Mechanical Etiology: The discomfort stems from an elevated dental filling, cracked tooth syndrome, or severe bruxism. In these presentations, pain is mediated by biomechanical pressure, rendering antibiotics ineffective.
Vital Irreversible Pulpitis: The nerve remains vital inside a closed dentinal chamber; elevated intrapulpal pressure drives the pain, which cannot be relieved by antimicrobials.
Bacterial Antimicrobial Resistance: Previous uncompleted or inappropriate antibiotic courses have selected for beta-lactamase-producing resistant bacterial strains.
Encapsulated, Undrained Purulent Abscess: Antibiotics cannot penetrate thick, avascular collections of pus within bone. The collection requires surgical incision and drainage to resolve.
Wisdom Tooth Pain Antibiotics: Pericoronitis Management
Evaluating wisdom tooth pain antibiotics for impacted third molars:
Bacterial Entrapment Beneath the Operculum: A partially erupted lower wisdom tooth is often covered by a mucosal tissue flap (operculum) that traps food particles. Anaerobic bacteria trigger pericoronitis, causing severe trismus and radiating throat pain.
Antibiotics Offer Only Temporary Relief: While antibiotics can calm surrounding soft-tissue inflammation over 48 hours, they do not resolve the impacted position of the tooth. Once the course concludes, food impaction inevitably triggers recurrent flare-ups.
Definitive Treatment: Clinical management requires operculectomy (excision of the overlying gingival flap) or surgical extraction of the impacted third molar.
Common Types of Antibiotics for Tooth Infections
Clinicians prescribe targeted agents based on oral microbial flora:
Penicillin Group (Amoxicillin / Amoxicillin + Clavulanic Acid): The first-line standard in dental medicine. Amoxicillin inhibits bacterial cell wall synthesis. Clavulanate is added (e.g., Augmentin) to overcome beta-lactamase-producing pathogens.
Clindamycin: The primary alternative for patients with confirmed penicillin or beta-lactam allergies. It exhibits osseous penetration, making it effective for alveolar bone infections.
Metronidazole: Often co-prescribed with amoxicillin to establish antimicrobial coverage against strict anaerobic periodontal and periapical pathogens.
Macrolides (Azithromycin / Clarithromycin): Considered in penicillin-allergic patients who cannot tolerate clindamycin.
Clinical Warning: Self-administering antibiotics without a prescription risks fatal anaphylaxis, organ toxicity, and global antimicrobial resistance. Antibiotics must be taken solely under professional direction.
The Hazards of Indiscriminate Antibiotic Use
Antimicrobial Resistance (Superbugs): Repeatedly using antibiotics to treat toothaches without dental care selects for resistant bacterial mutations, diminishing drug efficacy during systemic medical emergencies.
Gastrointestinal Dysbiosis: Broad-spectrum antibiotics disrupt beneficial gut microflora, predisposing patients to antibiotic-associated diarrhea, Clostridioides difficile colitis, and systemic candidiasis.
Delayed Treatment and Progressive Bone Loss: Temporarily suppressing pain with medications delays care while apical pathology quietly resorbs alveolar bone, converting a restorable tooth into a mandatory extraction.
Factors Influencing Treatment Cost
Health regulations prohibit advertising standardized clinical fees; costs depend on the required procedural intervention:
Primary Dental Procedure Required: Performing multi-visit microscopic root canal therapy versus surgical tooth extraction.
Surgical Incision and Drainage: Clinical management of fascial abscesses requiring intraoral incision, purulent evacuation, and surgical drain placement.
Intracanal Antimicrobial Technology: Incorporating diode lasers, ozone irrigation, or calcium hydroxide medicament placement within infected canals.
Third Molar Surgical Complexity: Simple non-surgical extraction versus complex osseous impaction surgery for a symptomatic wisdom tooth.
Antibiotics vs. NSAID Analgesics vs. Clinical Operative Care
Clinical Parameter | Systemic Antibiotics | NSAIDs (e.g., Ibuprofen) | Operative Dental Treatment |
Primary Action | Eradicates vulnerable bacteria | Suppresses pain pathways and edema | Mechanically removes infection focus |
Onset of Relief | Does NOT relieve pain (48-72h) | 30 to 45 minutes (Palliative) | Immediate relief upon intervention |
Definitive Cure? | No (Does not resolve internal decay) | No (Masks symptoms temporarily) | Yes (Permanent resolution) |
Intrapulpal Access | Zero penetration into necrotic pulp | Circulates in periapical tissues | Direct physical access into canals |
Health Risks | Resistance, gut dysbiosis, allergy | Gastric ulceration, renal load | Minimally invasive preservation |
Frequently Asked Questions (FAQ)
Can I buy antibiotics at a pharmacy to fix my toothache before seeing a dentist?
No. Most toothaches originate from vital pulp inflammation or localized pressure, which do not respond to antibiotics. Taking antibiotics without an exam exposes you to drug side effects without relieving pain. You should manage symptoms with an over-the-counter pain reliever and schedule a dental evaluation promptly.
Can a dentist extract a tooth or perform a root canal while it is actively abscessed?
Yes. Current clinical protocols prioritize immediate intervention. The outdated guidance to "take antibiotics for a week until the swelling disappears" is no longer standard practice unless severe trismus prevents access. Dentists achieve anesthesia through specialized techniques, open the tooth to drain the abscess, and relieve pain far more rapidly than medications alone.
If my tooth pain stops after 3 days of antibiotics, can I stop taking the medication?
No. If an antibiotic was prescribed for spreading infection, the full course (typically 5 to 7 days) must be completed. Discontinuing treatment prematurely allows partially suppressed, resilient bacteria to repopulate, leading to recurrent infections that resist first-line drugs.